on air: transmission

❦ “Infection control guidelines are fundamentally flawed: SARS-CoV-2 is airborne.”

Dr. K. Fearnley, NHS (England) (2023)

❦ on shared air and swimsuits

“Coughing into one’s sleeve while in shared air is like peeing into one’s swimsuit while in shared water.”

Malgorzata Gasperowicz (2023)

❦ on transmission of SARS-CoV-2

In late December 2021, the World Health Organization (WHO) belatedly admitted that SARS-CoV-2 – the virus that causes COVID-19 – is airborne.


SARS-CoV-2 is airborne, without any shadow of scientific doubt – and is primarily and predominantly transmitted via infectious microscopic aerosols through the air at both short and long range.


To extol hand-washing as a primary defence against SARS-CoV-2 infection is about as stupid as promising a two-pack-a-day smoker that the simple formula of soap + water will prevent chronic obstructive pulmonary disease and lung cancer.


Infographic illustrating short- and long-range airborne transmission of SARS-CoV-2 (COVID-19).


© 2025 The World Health Organization: ‘Indoor airborne risk assessment in the context of SARS-CoV-2’. [Graphic & document available from the WHO in PDF format only ➤]


Infections from direct body contact (holding hands or hugging), or from fomites (touching infected objects), are low-risk-to-negligible.


The airborne route, via short- and long-range aerosol, is extremely high risk and is unequivocally acknowledged to be the primary and dominant form of SARS-CoV-2 transmission.


📖 (13 Jan 2021 ~ Journal of Hospital Infection) Dismantling myths on the airborne transmission of severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2) ➤


❦ What are ‘aerosols’?


Aerosols are microscopic droplets suspended in the air, and move through a space much like cigarette smoke.


📖 (29 Oct 2020 ~ El País) A room, a bar and a classroom: how the coronavirus is spread through the air ➤


Without air-filtration or ventilation, infectious aerosols remain suspended in the air, becoming increasingly concentrated as time goes by.


© 2020 El País.


While larger droplets are commonly produced by coughing or sneezing, airborne aerosols are produced when a person exhales – including breathing, talking, singing, shouting, coughing or sneezing.


📖 (29 Oct 2020 ~ El País) A room, a bar and a classroom: how the coronavirus is spread through the air ➤


‘Six people get together in a private home, one of whom is infected.


Irrespective of whether safe distances are maintained, if the six people spend four hours* together talking loudly without wearing a face mask in a room with no ventilation, five will become infected.’


* Note: The infectiousness of SARS-CoV-2 has greatly increased since this 2020 scenario: infection times with current 2025/2026 variants can be counted in seconds and minutes rather than hours.


© 2020 El País.


And while heavier droplets fall to the ground within seconds, infectious aerosols can accumulate and stay airborne for hours in enclosed spaces.


📖 (17 Jun 2020 ~ El País) An analysis of three Covid-19 outbreaks: how they happened and how they can be avoided ➤


© 2020 El País.


Virus-laden aerosols can be present and cause infection long after an infected person has left a room, a shop, a hospital, a GP’s surgery, a pharmacy, a classroom, a bus, or a train.


Proven studies estimate that infectious aerosols can be present in an empty room for up to four hours, dependent on levels of ventilation and air-filtration, after an infected person has left the area.


📖 (17 Jun 2020 ~ El País) An analysis of three Covid-19 outbreaks: how they happened and how they can be avoided ➤


© 2020 El País.


‘Buildings play a critical role in minimising, or conversely exacerbating, the spread of airborne infectious diseases.


COVID-19 outbreaks largely occur indoors – and in-room long-range transmission beyond two meters (six feet) has been well-documented in conditions with no masking and low ventilation rates.’


(2021) The Lancet COVID-19 Commission ➤


📖 (29 Oct 2020 ~ El País) A room, a bar and a classroom: how the coronavirus is spread through the air ➤


‘The riskiest scenario [in a school] is a classroom with no ventilation and the teacher – Patient Zero – as the infected person.


If two hours* are spent in the classroom with an infected teacher, without taking any measures to counter the number of aerosols, there is the risk that up to 12 students could become infected.’


* Note: The infectiousness of SARS-CoV-2 has increased greatly since this early 2020 scenario: airborne person-to-person infections at either short- or long-range can be counted in seconds or minutes [with 2025/2026 variants] rather than hours.


© 2020 Luis Almodóvar / El País.


Infected asymptomatic people (people who are infectious but not showing symptoms, or up to 60% of cases) may not be aware that they are ejecting virus-laden aerosols into the air that you breathe.


© 2024 Protect our Province: New Brunswick (PoP NB) ➤


Other serious and potentially life-threatening airborne infectious diseases spread by aerosol include Measles, TB (Tuberculosis), Influenza, Highly Pathogenic Avian Influenza (HPAI/H5N1/‘Bird Flu’), Respiratory Syncytial Virus (RSV), Human Rhinovirus (HRV), Pneumonia, Adenovirus, Enterovirus, Severe Acute Respiratory Syndrome Coronavirus (SARS[-CoV-1]), and Middle East Respiratory Syndrome Coronavirus (MERS-CoV).


© 2024 CovidisAirborne.org ➤

❦ on invisible viral transmission, indirect chains of harm, learned negligence, and killing others

“I think a big problem is that many people’s conceptions of morality do not extend to invisible viral transmission and indirect chains of harm.


Punching someone in the face and bloodying their nose is unconscionable.


Killing a hundred people in a chain of negligent transmission?


No biggie.”

Blake Murdoch (2023) ➤

❦ on individual risk assessments, and sleeping public health bodies

“We cannot individually assess the risk of infection from poor indoor air quality (IAQ) [in public spaces]. Just as we cannot individually assess food safety in restaurants, or fire safety in cinemas, or aviation safety on flights.


These are in the control of others, and are regulated for our health and safety.”

Orla Hegarty (2024) ➤

❦ on biohazard levels, and bureaucratic cowardice

“Infection control guidelines are fundamentally flawed: SARS-CoV-2 is airborne.


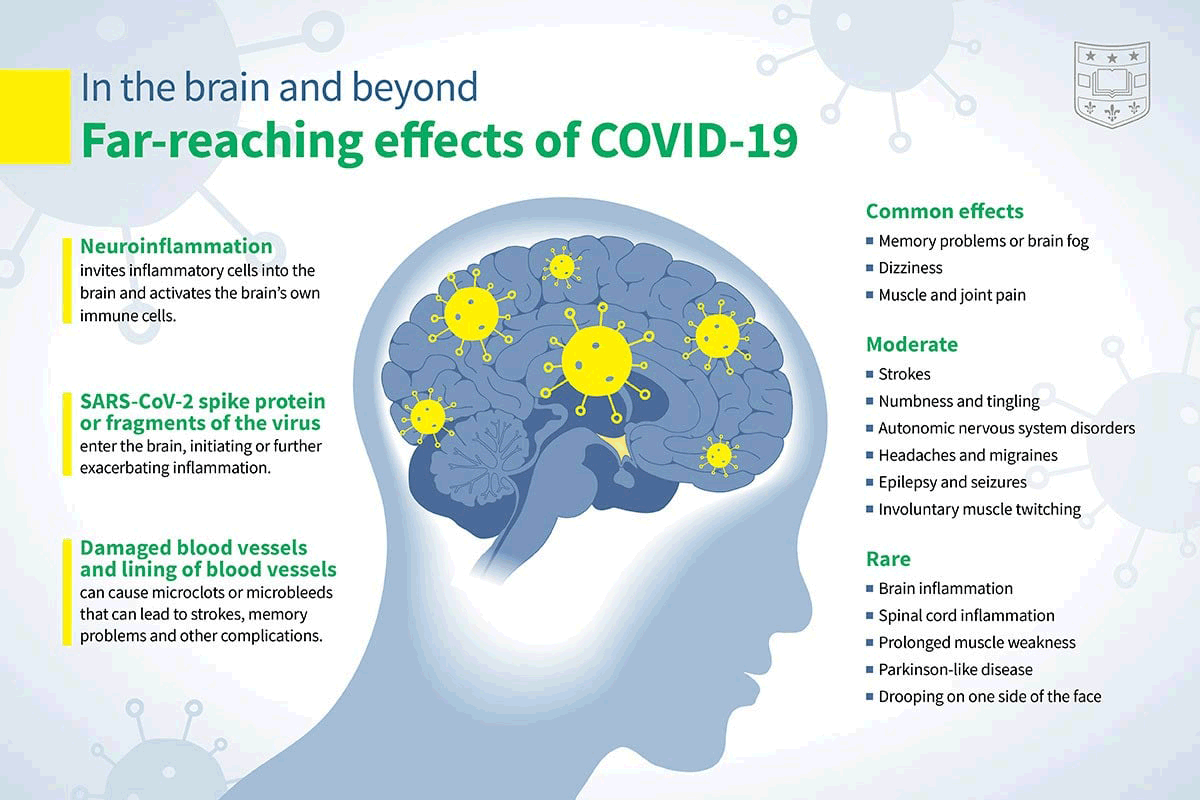
It is outrageous that three-and-a-half years into this pandemic, staff and patients are still, knowingly and repeatedly, being exposed to a Level-3 Biohazard – a virus known to cause brain damage and significantly increased risk of life-threatening blood complications even in those recovered.”


➲ Hazard Group 3 (HG3) ~ SARS-CoV-2 – the virus that causes COVID-19 – is classified as a Hazard Group 3 (HG3) pathogen.

The UK’s Health and Safety Executive (HSE) has designated SARS-CoV-2, the virus that causes COVID-19, a Hazard Group 3 (HG3) pathogen that can cause severe human disease.


The UK Health Security Agency (UKHSA) classifies SARS-CoV-2 as a notifiable organism, and COVID-19 as a notifiable disease [January 2026].


✾ Other HG3 examples include Andes orthohantavirus (‘Hantavirus’), Variant Creutzfeldt-Jakob disease agent (vCJD), Zika virus, Middle East respiratory syndrome-related coronavirus (MERS), Severe acute respiratory syndrome-related coronavirus 1 (SARS-CoV-1) (Genus Betacoronavirus), Human immunodeficiency viruses (HIV-1/HIV-2), Yellow fever, West Nile virus, Yersinia pestis (causative agent of Plague), and Mycobacterium tuberculosis (causative agent of TB).


➲ Hazard Group 4 (HG4) ~ The highest biohazard level.


Pathogens that pose a high risk of life-threatening disease for which there are no treatments.


HG4 examples include the Ebola virus, Marburg virus, and Lassa virus.


❦ Part 1: Human fodder for the ‘frontline’ (2021)

‘Our very serious concerns relate to the risk of aerosol/airborne infection; RCN and BMA members working in all settings are raising concerns that they are not adequately protected.


Our members are concerned that fluid repellent surgical face masks and face coverings, as currently advised in most general healthcare settings, do not protect against smaller more infective aerosols.’

Royal College of Nursing (RCN/UK) / British Medical Association (BMA) (21 Jan 2021) ➲

❦ on nosocomial (hospital-acquired or healthcare-associated) infections (HAIs)

“Every single case in which a person with Covid-19 infects another person in a healthcare setting – patient, relative, or hospital staff member – is a significant failure of hospital procedures.


Every single instance.”

Professor Steve Robson MPH MD PhD ~ President, Australian Medical Association (AMA) (2024)

❦ Part 2: Human fodder for the ‘frontline’ (2023)

‘Figures show that there has been a rise in COVID-19 cases and hospitalisations [in December 2023], and the RCN argues that without proper protections, ill health could continue to rise in nursing staff and impact their ability to deliver safe and effective patient care.


The RCN is urging healthcare employers to assess the risk posed by COVID-19 and put appropriate safeguards in place for patients and staff [regarding the newly-arrived variant JN.1].’

Royal College of Nursing (RCN) ~ (21 Dec 2023) ➲


‘We have heard from a range of multidisciplinary clinicians from across primary and secondary care express concern about the lack of availability of even the most basic protections in many settings when they are treating patients with confirmed or suspected COVID-19.


Ensuring the protection, so far as reasonably practicable, of staff who are vulnerable through exposure to the virus and any staff or patients who are individually susceptible and at risk of serious illness if they catch COVID-19 [nb: all are susceptible, throughout the age-range, and all are at cumulative risk of serious illness and death through reinfections], remains a paramount legal obligation.’

Professor Phil Banfield (BMA) & Dr. Barry Jones (CAPA) ~ (22 Dec 2023) ➲

Archives: Transmission

by ACCESS Newswire (Canada) • 28 October 2026
“We have engineered our way to cleaner rooms, cleaner sinks and cleaner surfaces. The air is the last and most important piece. Real-time disinfection of the air, continuously, while patients and staff are in the room, is the step that ties the whole system together.”
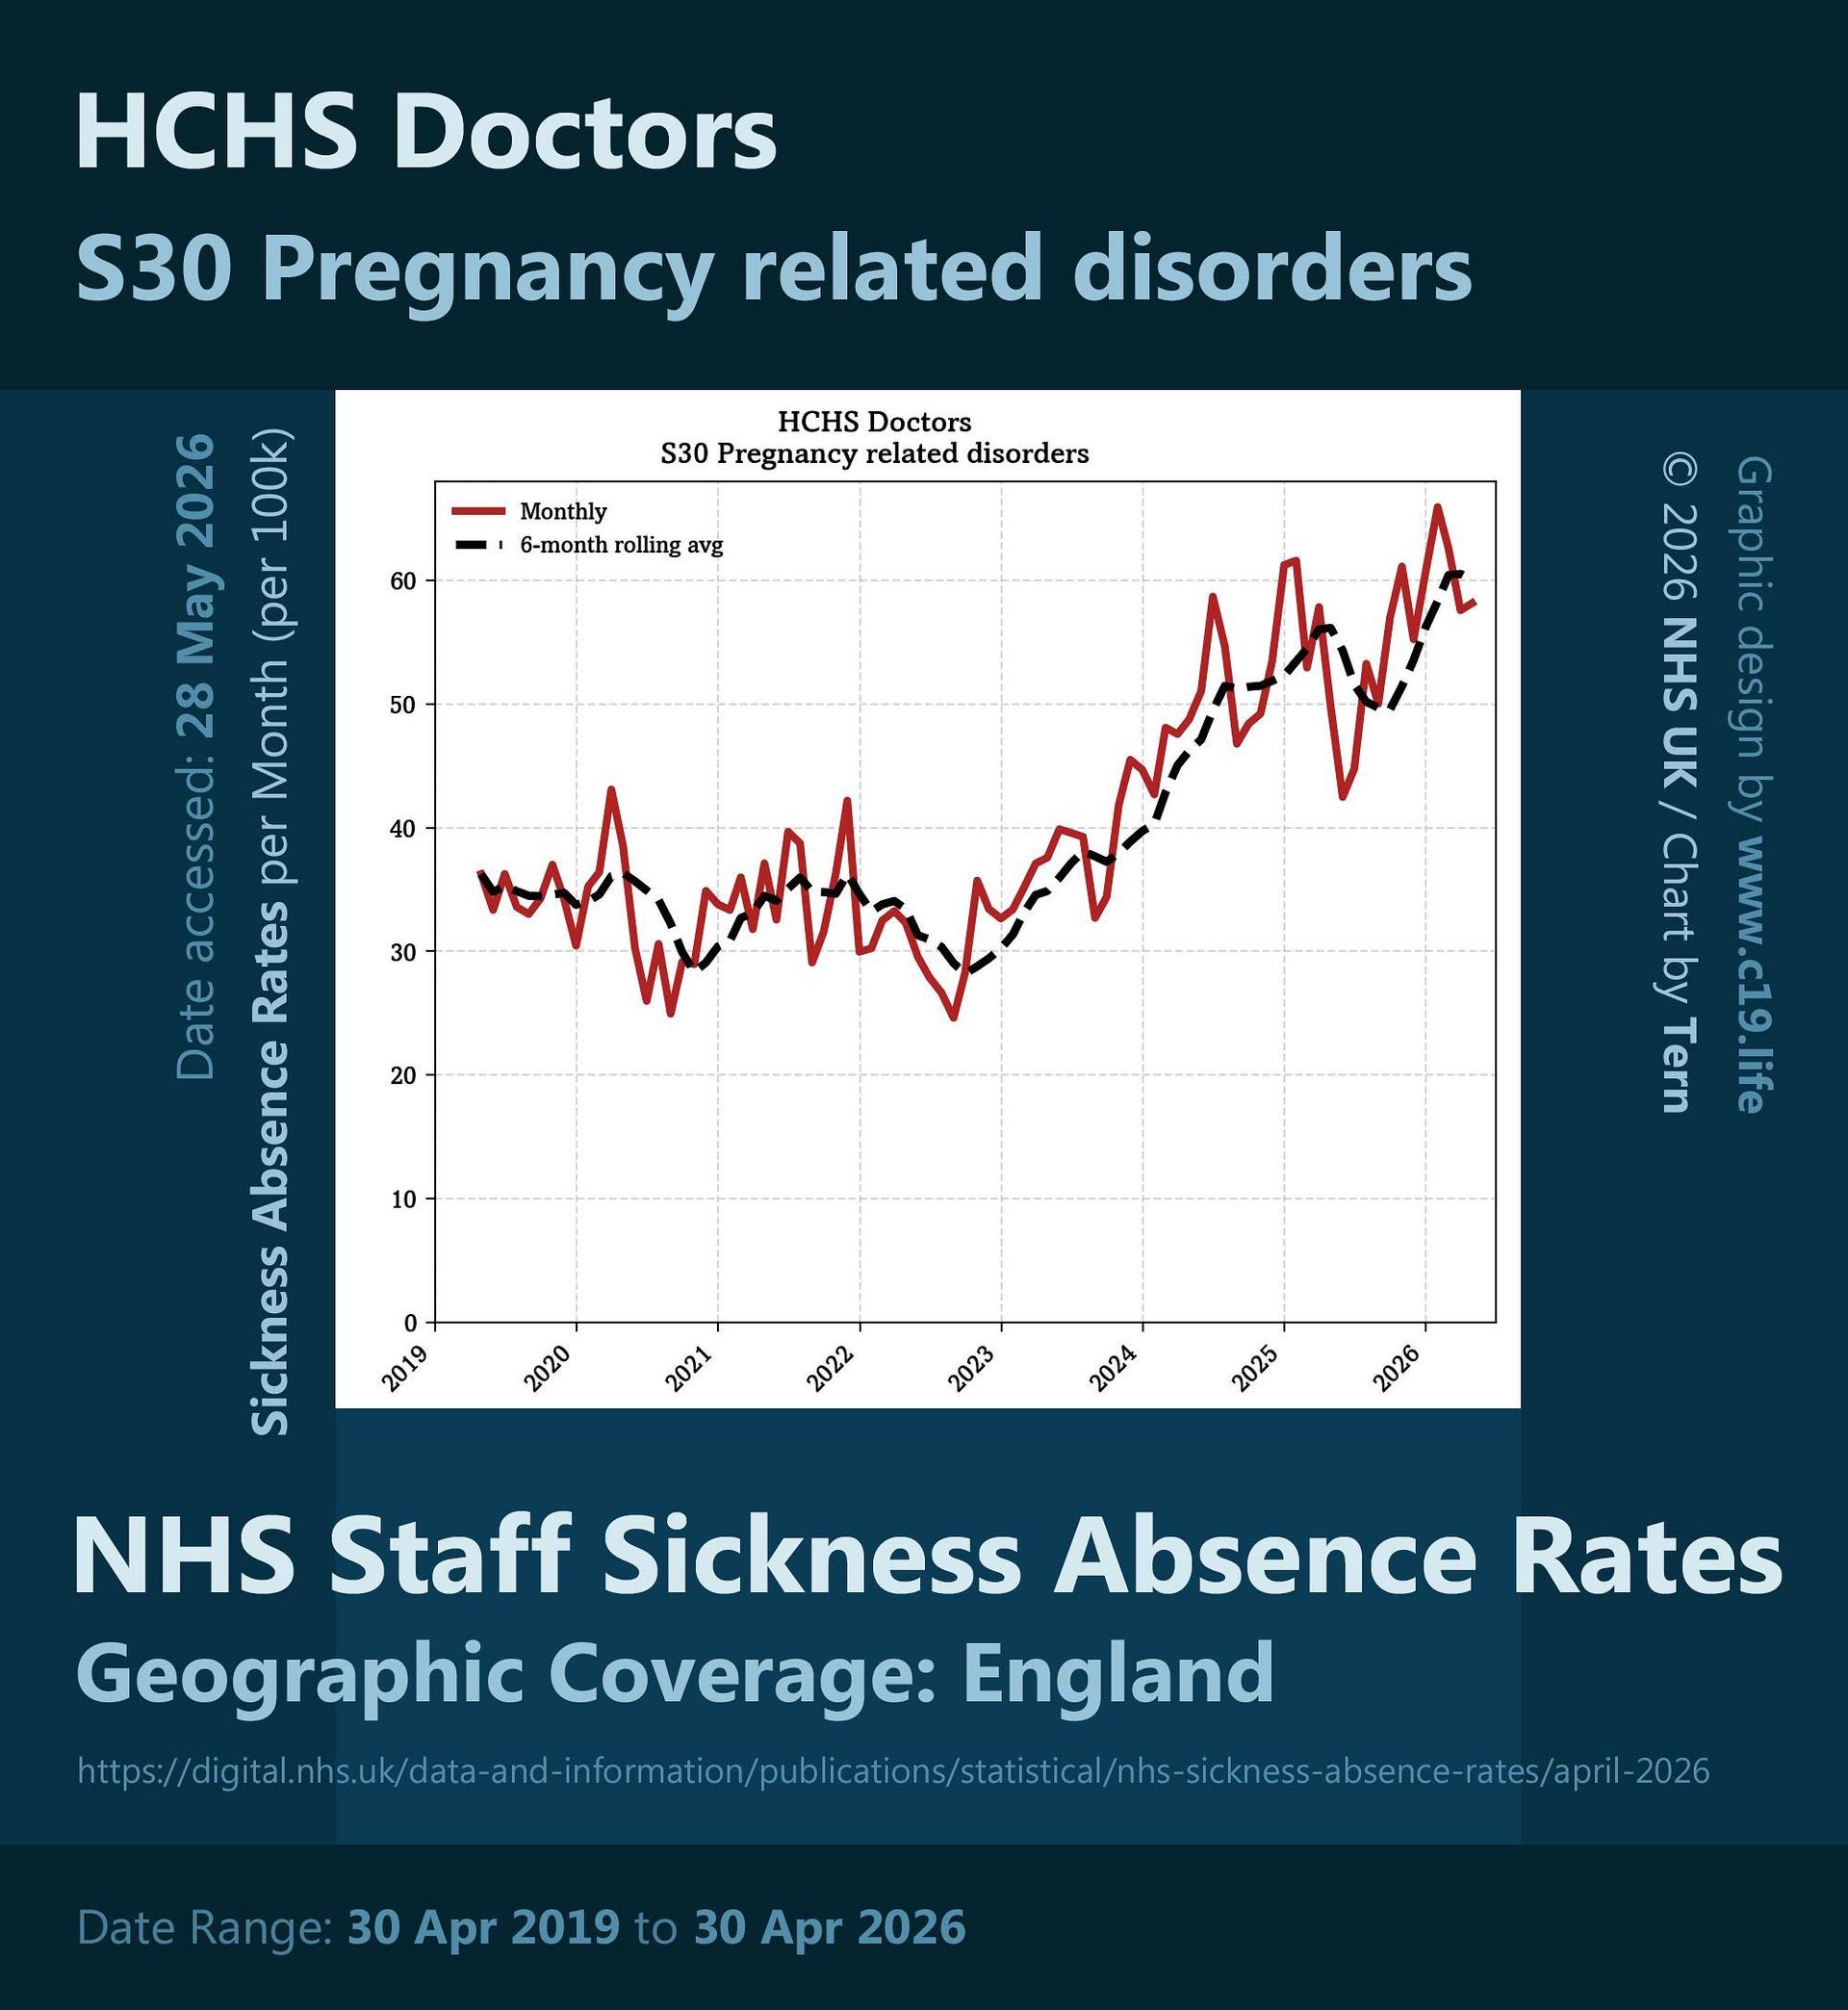
by National Health Service (NHS) England / Charts by Tern / Graphics by C19.Life • Data accessed 28 May 2026 • 18 August 2026
— “What?! Binned by a cold?” NHS (England) Staff Sickness Absence Rates per Month (per 100k) by Staff Group and Condition 2019–2026.
by C Raina MacIntyre, Noor Bari et al / Respiratory Medicine • 13 February 2026
‘Breathing, speaking, coughing, and sneezing produce infectious aerosols in clinical environments. Coughing produces more aerosols than endotracheal intubation.’
'The Approved List of biological agents'. Advisory Committee on Dangerous Pathogens / UKHSA.
by United Kingdom Health Security Agency (UKHSA) / Health & Safety Executive (HSE) / Control of Substances Hazardous to Health Regulations (COSHH) / C19.Life • Accessed 23 Oct 2025 • 23 October 2025
The Health and Safety Executive (HSE) has designated SARS-CoV-2, the virus that causes COVID-19, a Hazard Group 3 (HG3) pathogen that can cause severe human disease. The United Kingdom’s Health Security Agency (UKHSA) classifies SARS-CoV-2 as a notifiable organism, and COVID-19 as a notifiable disease.
by The British Occupational Hygiene Society ~ COSHH and Healthcare Respiratory Protection • 20 October 2025
‘FRSMs [Surgical Masks] have never been considered either adequate or suitable equipment for protection against inhalable or respirable risks under COSHH.’
by Cai et al / The Lancet: Infectious Diseases • 1 April 2025
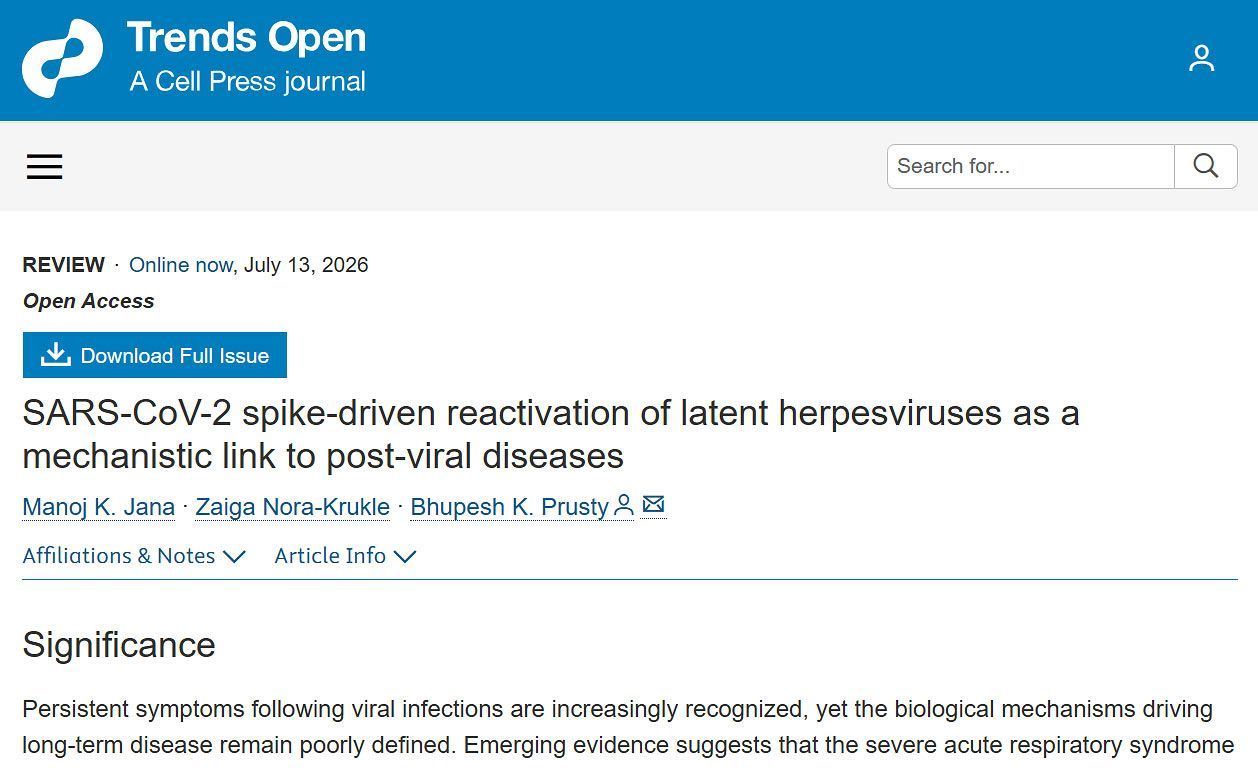
‘In the 12 months of follow-up, people with COVID-19 who did not require admission to hospital during the acute phase of infection had increased test-positivity rates for bacterial infections (in blood, urine, and respiratory cultures) and viral diseases (including Epstein–Barr virus, herpes simplex virus reactivation, and respiratory viral infections). Compared with people admitted to hospital for seasonal influenza, those admitted for COVID-19 had higher rates of admission to hospital for infectious illnesses (increased risk of 24%), admission to hospital for sepsis (increased risk of 35%), and in-hospital use of antimicrobials (increased risk of 23%).’
by Dr. Noor Bari, Emergency Medicine ❂ NextStrain.org • 29 October 2024
❦ “If you are letting yourself get infected and taking no precautions against passing it on, you are not a passive bystander for your next infection. You’ve participated in creating it.”
by Dempsey et al / BMJ Journals ~ Occupational and Environmental Medicine • 8 October 2024
‘This study included 5248 healthcare workers. While 33.6% reported prolonged COVID-19 symptoms consistent with PCS, only 7.4% reported a formal diagnosis of PCS. Fatigue, difficulty concentrating, insomnia, and anxiety or depression were the most common PCS [Post-COVID-19 Syndrome] symptoms. Baseline risk factors for reporting PCS included screening for common mental disorders, direct contact with COVID-19 patients, pre-existing respiratory illnesses, female sex and older age.’
‘The Ventilation and Warming of School Buildings’ (1887) by Gilbert B. Morrison.
by Gilbert B. Morrison (1887) • 10 April 2024
‘In those school-rooms where ventilation is imperfect and the air impure, six sevenths of the money expended to educate a child is wasted.’ ❂ The Ventilation and Warming of School Buildings (1887) By Gilbert B. Morrison Published by D. Appleton and Company, New York. 1887. Accessed 10 Apr 2024 Preface (p.xxii) ❦ ‘I am fully convinced that people are prematurely dying by thousands simply from a lack of correct and positive convictions concerning impure air; for, when the true nature of a danger is fully appreciated, the requisite means to avert it will generally be found.’ ❂ Chapter II: The Effects Of Breathing Impure Air (pp.20-23) ❦ ‘Impure air is also believed by the best authorities to be one of the principal causes of epidemics. Dr. Carpenter, than whom there is no abler authority, says: “It is impossible for anyone who carefully examines the evidence to hesitate for a moment in the conclusion that the fatality of epidemics is almost invariably in precise proportion to the degree in which an impure atmosphere has been habitually respired.” The Board of Health of New York conclude that forty per cent of all deaths are caused by breathing impure air. In view of such alarming facts, this same board declares: “Viewing the causes of preventable diseases, and their fatal results, we unhesitatingly state that the first sanitary want in New York and Brooklyn is ventilation .” Direct experiment proves that the air in our school-rooms is impure in almost all cases, and in a majority of them to a degree far beyond the danger line. In view of these facts, and the results as proved by the authorities above cited, why is it regarded by the public with such indifference? When a school-house is blown down by a hurricane, killing and maiming a score of children, it is justly regarded as a great calamity; a vacation is given to quiet the excited fears of parents and children; investigating committees are appointed to locate the responsibility, and the faces of the whole populace are blanched with apprehension. Why is this? Why does the intelligent parent send his child to a school-room poorly ventilated and crowded with children, some of whom are breathing into a stagnant air the germs of disease and death, while others, from unwashed bodies, are delivering into it their deadly emanations, and all without a protest on the part of those even who provide proper hygienic conditions at home? It is because the effects of the one are immediate, occupy little time, the number killed can be actually counted, and the exact magnitude of the calamity estimated all at once. In the other case the process is slower, but of far greater extent; the actual results are by the general public less definitely known, and custom and attention to other matters divert the attention, and the deadly destruction of the innocents by impure air goes on silently, constantly, and powerfully. While noisy demonstrations like that of the cyclone attract attention, and inspire fear and terror, it is in the silent forces that the danger lies. Nature’s most destructive forces, as well as her strongest constructive ones, are silent in their operations; but when Science detects a silent, insidious enemy to human welfare, it is not only our duty to assume an attitude of self-defense and self-protection, but it should be regarded as folly not to do so.’ ❦ On high CO₂ levels connected to poor performance in schools: ‘The effects of breathing impure air thus far considered are pathological, but it has its pedagogical and economical aspects. Every observing teacher knows the immediate relation between the vitiated air in the school-room and the work he wishes the pupils to perform. Much of the disappointment of poor lessons and the tendency to disorder are due directly to this cause. The brain unsupplied with a proper amount of pure blood [oxygen] refuses to act, and the will is powerless to arouse the flagging energies; the general feeling of discomfort, dissatisfaction, and unrest which always accompanies a bad state of the blood. From an economical standpoint it would, of course, be impossible to estimate the financial waste of breathing impure air, but it can not but be enormous. In any discussion of the feasibility of incurring the additional expense of the most perfect ventilation, this loss occasioned by the want of such ventilation must not be ignored.’ ❂ Chapter III: The Air (pp.25-26) ❦ On ventilation, air filtration, and the super-spreading of diverse diseases in classrooms: ‘Wherever an unusual amount of unwholesome matter is being evolved, there especially should the purifying conditions be present; air in such places, to remain pure, must be changed in rapid succession, in order that dilution, diffusion, and oxidation may fulfill their legitimate functions. In a school-room the contaminating process can not but be rapid, and wherever ample provision is not made for rapidly changing the air of the room a dangerous condition of affairs is sure to exist. Bacteria of many forms, and spores of fungi, are also found in the air, and all these organisms are known to thrive in the organic impurities found in the air.’ ❂ Chapter IV: Examination Of The Air (p.33) ❦ On measuring CO₂ levels as a proxy to establishing content of (infectious) re-breathed air: ‘A complete analysis of impure air comprehends the quantitative and qualitative tests for carbonic [sic] dioxide, free ammonia, and other nitrogenous matter, oxidizable matters, nitrous and nitric acids, and hydrogen sulphide; but for ordinary practical purposes the determination of the CO₂ is by far the most important, and is ordinarily the only one which need be made. While the poisonous qualities of the air are not wholly due to the presence of the CO₂ per se, the amount of this gas found to be present is, in air made impure by respiration, generally a good measure for other impurities to which the poisonous quality is principally due. Owing to this fact, a careful test for the amount of CO₂ contained in a given atmosphere is generally the only one which need be made where air is tested merely to determine its respiratory purity.’ ❂ 📖 (Accessed 10 Apr 2024 ~ D. Appleton & Company / Google Books) The Ventilation and Warming of School Buildings ➤ ❂ My thanks to Maarten De Cock for alerting me to this gem of a book. ➲
COVID is Airborne
by Jonathan Mesiano-Crookston... et al • 4 March 2024
❦ A comprehensive collection of review articles from 1987 to 2022 regarding airborne transmission of pathogens, curated by Jonathan Mesiano-Crookston. ❂ Accessed : 4 March 2024 . 📖 (November 2022 ~ Geoscience Frontiers) Aerosol Transmission of Human Pathogens: From Miasmata to Modern Viral Pandemics and Their Preservation Potential in the Anthropocene Record ➤ 📖 (21 Aug 2022 ~ Indoor Air) What were the historical reasons for the resistance to recognizing airborne transmission during the COVID-19 pandemic? ➤ 📖 (31 Jan 2022 ~ Indoor Air: Editorial) Hypothesis: All respiratory viruses (including SARS-CoV-2) are aerosol-transmitted ➤ 📖 (November 2021 ~ Interface Focus) How Did We Get Here: What Are Droplets and Aerosols and How Far Do They Go? A Historical Perspective on the Transmission of Respiratory Infectious Diseases➤ 📖 (27 Aug 2021 ~ Science ) Airborne Transmission of Respiratory Viruses ➤ 📖 (August 2021 ~ Nature Reviews: Microbiology) Transmissibility and Transmission of Respiratory Viruses ➤ 📖 (July 2021 ~ Annual Review of Biomedical Engineering) Fluid Dynamics of Respiratory Infectious Diseases ➤ 📖 (14 May 2021 ~ Science) A Paradigm Shift to Combat Indoor Respiratory Infection ➤ 📖 (1 May 2021 ~ The Lancet) Ten Scientific Reasons in Support of Airborne Transmission of SARS-CoV-2 ➤ 📖 (18 Jan 2021 ~ Clinical Infectious Diseases) Airborne Transmission of SARS-CoV-2: What We Know ➤ 📖 (12 Jan 2021 ~ The Journal of Hospital Infection) Dismantling Myths on the Airborne Transmission of Severe Acute Respiratory Syndrome Coronavirus-2 (SARS-CoV-2) ➤ 📖 (1 Jan 2021 ~ Canadian Medical Association Journal) Mitigating Airborne Transmission of SARS-CoV-2 ➤ 📖 (November 2020 ~ Environment International) Aerosol Transmission of SARS-CoV-2? Evidence, Prevention and Control➤ 📖 (16 Oct 2020 ~ Science) Airborne Transmission of SARS-CoV-2 ➤ 📖 (1 Sep 2020 ~ Environment International) How Can Airborne Transmission of COVID-19 Indoors Be Minimised? ➤ 📖 (August 2020 ~ Anaesthesia) Airborne Transmission of Severe Acute Respiratory Syndrome Coronavirus-2 to Healthcare Workers: A Narrative Review ➤ 📖 (6 July 2020 ~ Clinical Infectious Diseases) It Is Time to Address Airborne Transmission of Coronavirus Disease 2019 (COVID-19) ➤ 📖 (June 2020 ~ Environment International) Airborne Transmission of SARS-CoV-2: The World Should Face the Reality➤ 📖 (May 2020 ~ Risk Analysis) Consideration of the Aerosol Transmission for COVID‐19 and Public Health➤ 📖 (16 April 2020 ~ The Journal of Infectious Diseases) Airborne or Droplet Precautions for Health Workers Treating Coronavirus Disease 2019? ➤ 📖 (26 March 2020 ~ JAMA) Turbulent Gas Clouds and Respiratory Pathogen Emissions: Potential Implications for Reducing Transmission of COVID-19 ➤ 📖 (28 Aug 2019 ~ Encyclopedia of Microbiology) Airborne Infectious Microorganisms ➤ 📖 (31 Jan 2019 ~ BMC Infectious Diseases) Recognition of Aerosol Transmission of Infectious Agents: A Commentary➤ 📖 (September 2016 ~ American Journal of Infection Control) Generic Aspects of the Airborne Spread of Human Pathogens Indoors and Emerging Air Decontamination Technologies ➤ 📖 (15 Nov 2011 ~ Advances in Preventive Medicine) Preventing Airborne Disease Transmission: Review of Methods for Ventilation Design in Health Care Facilities ➤ 📖 (October 2006 ~ The Journal of Hospital Infection) Factors Involved in the Aerosol Transmission of Infection and Control of Ventilation in Healthcare Premises ➤ 📖 (January 1987 ~ Critical Reviews in Environmental Control) Spread of Viral Infections by Aerosols➤ ✾ © 2024 Jonathan Mesiano-Crookston ➤
Infographic illustrating short- and long-range airborne aerosol transmission of SARS-CoV-2 COVID-19.
by C19.Life • 28 February 2024
In late December 2021 , the World Health Organization ( WHO ) belatedly admitted that SARS-CoV-2 – the virus that causes COVID-19 – is airborne . SARS-CoV-2 is airborne , without any shadow of scientific doubt – and is primarily and predominantly transmitted via infectious microscopic aerosols through the air at both short and long range . To extol hand-washing as a primary defence against SARS-CoV-2 infection is about as stupid as promising a two-pack-a-day smoker that the simple formula of soap + water will prevent chronic obstructive pulmonary disease and lung cancer.
by Florence Nightingale (1859/1860) • 19 February 2024
‘The very first canon of nursing... the first essential to the patient... is this: to keep the air he breathes as pure as the external air, without chilling him .’ ❂ Notes on Nursing (1860 edition) By Florence Nightingale First Published 1859. Revised edition reprinted in 1860 by Harrison of Pall Mall Accessed 19 Feb 2024 ❦ Chapter I – Ventilation and Warming ‘The very first canon of nursing, the first and the last thing upon which a nurse’s attention must be fixed, the first essential to the patient, without which all the rest you can do for him is as nothing, with which I had almost said you may leave all the rest alone, is this: TO KEEP THE AIR HE BREATHES AS PURE AS THE EXTERNAL AIR, WITHOUT CHILLING HIM. Yet what is so little attended to? Even where it is thought of at all, the most extraordinary misconceptions reign about it. Even in admitting air into the patient’s room or ward, few people ever think where that air comes from. It may come from a corridor into which other wards are ventilated, from a hall, always unaired, always full of the fumes of gas, dinner, of various kinds of mustiness; from an underground kitchen, sink, wash-house, water-closet, or even, as I myself have had sorrowful experience, from open sewers loaded with filth; and with this the patient’s room or ward is aired, as it is called – poisoned, it should rather be said. Always air from the air without, and that, too, through those windows, through which the air comes freshest. From a closed court, especially if the wind do not blow that way, air may come as stagnant as any from a hall or corridor. I know an intelligent humane house surgeon who makes a practice of keeping the ward windows open. The physicians and surgeons invariably close them while going their rounds; and the house surgeon, very properly, as invariably opens them whenever the doctors have turned their backs. I have known a medical officer keep his ward windows hermetically closed, thus exposing the sick to all the dangers of an infected atmosphere, because he was afraid that, by admitting fresh air, the temperature of the ward would be too much lowered. This is a destructive fallacy. To attempt to keep a ward warm at the expense of making the sick repeatedly breathe their own hot, humid, putrescing atmosphere is a certain way to delay recovery or to destroy life.’ ❂ ‘I have known cases of hospital pyæmia quite as severe in handsome private houses as in any of the worst hospitals, and from the same cause, viz., foul air. Yet nobody learnt the lesson. Nobody learnt anything at all from it.’ ❂ ✪ C-19: On schools ‘Of all places, public or private schools, where a number of children or young persons sleep in the same dormitory * , require this test of freshness to be constantly applied.’ * [ C-19 Note: You might substitute ‘sleep’ and ‘dormitory’ with ‘study’ and ‘classroom’ in this section.] ‘If it be hazardous for two children to sleep together in an unventilated bedroom, it is more than doubly so to have four, and much more than trebly so to have six under the same circumstances. People rarely remember this; yet, if parents were as solicitous about the air of school bedrooms as they are about the food the children are to eat, and the kind of education they are to receive, at school, depend upon it due attention would be bestowed on this vitally important matter, and they would cease to have their children sent home either ill, or because scarlet fever or some other “current contagion” had broken out in the school. There are schools where attention is paid to these things, and where “children’s epidemics” are unknown.’ ❂ ✪ C-19: Offices, shops, factories, and other workplaces ‘How much sickness, death, and misery are produced by the present state of many factories, warehouses, workshops, and workrooms!’ ‘How much sickness, death, and misery are produced by the present state of many factories, warehouses, workshops, and workrooms! The places where poor dressmakers, tailors, letter-press printers, and other similar trades have to work for their living, are generally in a worse sanitary condition than any other portion of our worst towns. Many of these places of work were never constructed for such an object. They are badly adapted garrets, sitting-rooms, or bedrooms, generally of an inferior class of house. No attention is paid to cubic space or ventilation. The poor workers are crowded on the floor to a greater extent than occurs with any other kind of over-crowding. The constant breathing of foul air, saturated with moisture, and the action of such air upon the skin renders the inmates peculiarly susceptible of the impression of cold, which is an index indeed of the danger of pulmonary disease to which they are exposed. The result is, that they make bad worse, by over-heating the air and closing up every cranny through which ventilation could be obtained. In such places, and under such circumstances of constrained posture, want of exercise, hurried and insufficient meals, long exhausting labour and foul air – is it wonderful that a great majority of them die early of chest disease, generally of consumption? Intemperance is a common evil of these workshops. The men can only complete their work under the influence of stimulants, which help to undermine their health and destroy their morals, while hurrying them to premature graves. Employers rarely consider these things. Healthy workrooms are no part of the bond into which they enter with their work-people. They pay their money, which they reckon their part of the bargain. And for this wage the workman or workwoman has to give work, health, and life. Do men and women who employ fashionable tailors and milliners ever think of these things? And yet the master is no gainer. His goods are spoiled by foul air and gas fumes, his own health and that of his family suffers, and his work is not so well done as it would be, were his people in health. And the time will come when it will be found cheaper to supply shops, warehouses, and work-rooms with pure air than with foul air.’ ‘And the time will come when it will be found cheaper to supply shops, warehouses, and work-rooms with pure air than with foul air.’ ❂ ✪ C-19: On ‘air-tests’, and measuring CO₂ as a proxy for estimating prevalence of airborne disease indoors ‘Dr. Angus Smith’s air-test, if it could be made of simple application, would be invaluable to use in every sleeping and sick room. Just as without the use of a thermometer no nurse should ever put a patient into a bath, so, if this air-test were made in some equally simple form, should no nurse, or mother, or superintendent, be without it in any ward, nursery, or sleeping-room. But to be used, the air-test must be made as simple a little instrument as the thermometer, and both should be self-registering. ‘...the air-test must be made as simple a little instrument as the thermometer, and both should be self-registering.’ The senses of nurses and mothers become so dulled to foul air that they are perfectly unconscious of what an atmosphere they have let their children, patients, or charges sleep in. But if the tell-tale air-test were to exhibit in the morning, both to nurses and patient and to the superior officer going round, what the atmosphere has been during the night, I question if any greater security could be afforded against a recurrence of the misdemeanour.’ ❂ ✪ C-19: ... And back to the school-room, testing its air, and combatting airborne pathogens ‘And, oh! the crowded national school! where so many children’s epidemics have their origin; and the crowded, unventilated work-room, which sends so many consumptive men and women to the grave; what a tale its air-test would tell! We should have parents saying, and saying rightly, “I will not send my child to that school. I will not trust my son or my daughter in that tailor’s or milliner’s workshop, the air-test stands at ‘Horrid.’” ‘We should have parents saying, and saying rightly, “I will not send my child to that school... the air-test stands at Horrid .”’ And the dormitories of our great boarding schools! Scarlet fever would be no more ascribed to contagion but to its right cause, the air-test standing at “Foul.” We should hear no longer of “mysterious dispensations,” nor of “plague and pestilence” being “in God’s hands,” when, so far as we know, He has put them into our own. The little air-test would both betray the cause of these “mysterious pestilences,” and call upon us to remedy it.’ ❂ ❦ Chapter II – Health of Houses ‘There are five essential points in securing the health of houses:– Pure air. Pure water. Efficient drainage. Cleanliness. Light. Without these, no house can be healthy. And it will be unhealthy just in proportion as they are deficient. To have pure air, your house must be so constructed as that the outer atmosphere shall find its way with ease to every corner of it. ‘To have pure air, your house must be so constructed as that the outer atmosphere shall find its way with ease to every corner of it.’ House architects hardly ever consider this. The object in building a house is to obtain the largest interest for the money, not to save doctor’s bills to the tenants. But, if tenants should ever become so wise as to refuse to occupy unhealthily constructed houses, and if Insurance Companies should ever come to understand their interest so thoroughly as to pay a Sanitary Surveyor to look after the houses where their clients live, speculative architects would speedily be brought to their senses. As it is, they build what pays best. And there are always people foolish enough to take the houses they build. And if in the course of time the families die off, as is so often the case, nobody ever thinks of blaming any but Providence for the result. Ill-informed medical men aid in sustaining the delusion, by laying the blame on “current contagions”. Badly constructed houses do for the healthy what badly constructed hospitals do for the sick.’ ‘Badly constructed houses do for the healthy what badly constructed hospitals do for the sick.’ ❂ ❦ Conclusion ‘The whole of the preceding remarks apply even more to children and to puerperal women than to patients in general. They also apply to the nursing of surgical, quite as much as to that of medical cases. Indeed, if it be possible, cases of external injury require such care even more than sick. In surgical wards, one duty of every nurse certainly is prevention. Fever, or hospital gangrene, or pyæmia, or purulent discharge of some kind may else supervene. If she allows her ward to become filled with the peculiar close fœtid smell, so apt to be produced among surgical cases, especially where there is great suppuration and discharge, she may see a vigorous patient in the prime of life gradually sink and die where, according to all human probability, he ought to have recovered. The surgical nurse must be ever on the watch, ever on her guard, against want of cleanliness, foul air, want of light, and of warmth.’ ‘In surgical wards, one duty of every nurse certainly is prevention.’ ❂ 📖 (Accessed 19 Feb 2024 ~ Original text copied from FiftyWordsForSnow.com) Notes on Nursing (1860) ➤ 📖 (Accessed 19 Feb 2024 ~ Original scanned pages from Google Books) Notes on Nursing (1860) ➤ ❂
by George Monbiot • 22 January 2024
❦ “I was in hospital for tests this morning. A nurse asked me: — “How come so many people are wearing masks? Is there something I don’t know?” I almost lost the power of speech.”
by Professor Steve Robson MPH MD PhD ~ President, Australian Medical Association (AMA) • 20 January 2024
❦ “Every single case in which a person with COVID-19 infects another person in a healthcare setting – patient, relative, or hospital staff member – is a significant failure of hospital procedures. Every single instance .”
by Orla Hegarty / WHO (Europe) • 18 January 2024
❦ “We cannot individually assess the risk of infection from poor indoor air quality (IAQ) [ in public spaces ] . Just as we cannot individually assess food safety in restaurants, or fire safety in cinemas, or aviation safety on flights. These are in the control of others, and are regulated for our health and safety.”
AI image of an Ink-bottle with a double-edged pencil, made with Wombo by c19.life.
by Dr. David Tomlinson, NHS Consultant Cardiologist • 9 January 2024
❦ “I met a nice lady – a ward patient – yesterday who, seeing my [ FFP3 ] respirator [ high-filtration ‘mask’ ] , promptly put on her surgical mask. So instead of diving straight in to asking what was most concerning her and how I could help, I opened up a bit about infection control in hospitals. I explained how, because of a lack of respirators, March 2020 saw NHS leaders downgrade PPE for all non-ICU staff. ❂ PPE : Personal Protective Equipment. I then reminded her of the amazing DHSC 2020 and 2021 campaigns on airborne transmission of SARS2 (the green-and-black smoke ones) – and I had to point out that every IPC Lead Nurse had since had to switch off their brain and forget what they knew – and while at work, to only protect ICU staff. ❂ DHSC : Department of Health and Social Care (UK). ❂ IPC : Infection Prevention and Control. I explained that the individuals responsible for the original IPC downgrade were now authors of the national manual on IPC (NIPCM), which sets the standard for infection control in hospitals, and this manual states that airborne transmission is ‘not a thing’ for SARS2 (AGP only). ❂ NIPCM : The UK’s National Infection Prevention and Control Manual. ❂ AGP : Aerosol-Generating Procedure, ie. intubation. So hospitals are destined to be unsafe spaces thanks to the NIPCM, and the surgical mask that she was wearing was OK (ish) to help protect me – but did very little to reduce her risk of SARS2 inhalation. However, she was in a single room (an extra, and not meant as a ward-bed space – but you know, >100% occupancy forever means that you need to use your imagination) – and she already had the window open. She was appalled at what healthcare workers were being put through. She was appalled at the on-going lies. She was appalled at the possible level of harm to patients and staff from such lies. She then went on to tell me how a weekend visitor of hers had just tested positive for Covid. She was worried that they had hugged and chatted, and that she might have got infected. She’s a switched on lady, too. Lives with a medic who has the windows open all the time (“It’s freezing at home”). So I explained about the CleanAirStars.com site. About HEPA filtration being a low energy and low-cost way to remove all airborne pathogens , and to make home a safer place for... • Covid • Flu • RSV • Norovirus • Fungi, etc. etc. The list goes on and on. — “Wow, that’s like magic!” We had a very nice chat. And then we talked about her heart. I just wish I could have this same conversation with each and every NHS CEO and IPC Lead Nurse. I’d ask some questions. I’d want to know why they aren’t protecting staff as they should. I’d want to know why they aren’t protecting patients as they should. I’d want them to know that they are in breach of UK legislation . And I’d want to look them in the eye and ask them to show compassion to the powerless: to staff, and patients. Help us please. Do whatever you can to counter the lies, and to help protect the NHS. Thank-you.” ✾ © 2024 Dr. David Tomlinson (NHS Consultant Cardiologist) ➤
by Professor Phil Banfield (BMA) & Dr. Barry Jones (CAPA) • 22 December 2023
‘It is accepted that COVID-19 can be and is spread by the airborne route. The recent evidence given at the UK COVID-19 Inquiry clearly shows that aerosol transmission is a significant, and almost certainly the dominant, route of transmission for COVID-19.’ The British Medical Association (22 Dec 2023)
by Royal College of Nursing (RCN) (UK) • 21 December 2023
‘The RCN is urging healthcare employers to assess the risk posed by COVID-19 and put appropriate safeguards in place for patients and staff. WHO [has] advised healthcare workers and health facilities to implement universal masking in health facilities, as well as appropriate masking, respirators and other personal protective equipment for health workers caring for suspected and confirmed COVID-19 patients; and to improve ventilation in health facilities.’ ✾ ❦ We’ve contacted chief nursing officers in all four UK countries and the UKHSA to find out what action will be taken in response to WHO’s statement on a new COVID-19 variant of interest. The RCN is asking for a revision to current guidelines , to introduce universal implementation of the two measures advised by the World Health Organization (WHO) to help protect healthcare staff against COVID-19. Earlier this week, in light of the new COVID JN.1 variant, WHO advised healthcare workers and health facilities to: implement universal masking in health facilities , as well as appropriate masking , respirators and other personal protective equipmen t for health workers caring for suspected and confirmed COVID-19 patients ; improve ventilation in health facilities . The existing national infection prevention and control manuals don’t require standardised masking for COVID-19, and decisions on respiratory protective equipment are left to local risk assessments. This is now inconsistent with WHO’s latest advice . We also have concerns about the adequacy of ventilation in general ward and outpatient areas within hospital buildings and believe that action must be taken to assess and improve this. Although evidence suggests that the global public health risks from the new variant are low, WHO has warned that onset of winter could increase the burden of respiratory infections in the Northern hemisphere. This comes when there are already unsustainable pressures on the health service. Figures show that there has been a rise in COVID-19 cases and hospitalisations , and the RCN argues that without proper protections , ill health could continue to rise in nursing staff and impact their ability to deliver safe and effective patient care . WHO has advised that it is continuously monitoring the evidence and will update the JN.1 risk evaluation as needed. The RCN is urging healthcare employers to assess the risk posed by COVID-19 and put appropriate safeguards in place for patients and staff . Our COVID-19 workplace risk assessment toolkit aims to help assess and manage the risks associated with respiratory infections such as COVID-19, highlights the duties of nursing staff in specific roles (such as health and safety reps), has advice for employers and leaders, and provides the latest information on risk assessment. ❂ 📖 (21 Dec 2023 ~ Royal College of Nursing / RCN Magazine) COVID JN.1 variant: RCN seeks assurance on new PPE advice ➤ © 2023 Royal College of Nursing (RCN).
by Conor Browne • 15 December 2023
❦ “Unless we reduce the transmission of Covid-19 through societal non-pharmaceutical interventions (such as cleaning indoor air) and/or the deployment and uptake of second-generation vaccines, attrition of healthcare will reach a tipping point. This tipping point – which may well happen within the next year – will lead to a global decrease in quality of available healthcare services, which in turn will lead to increased morbidity and mortality from all causes. Every government needs to reduce transmission. The denial of this problem will not change the outcome. Policymakers need to understand this.” ❂ © 2023 Conor Browne ➲
by Malgorzata Gasperowicz • 12 December 2023
❦ “Coughing into one’s sleeve while in shared air is like peeing into one’s swimsuit while in shared water.”
Show More Articles

❦ on transmission: scientific papers & media articles

✒ 2023

📖 (15 Sep 2023 ~ CIDRAP/University of Minnesota) Study: Hospital wastewater system a 'highway' for resistant bacteria ➤


❂


📖 (8 Sep 2023 ~ Pre-print) Quantity of SARS-CoV-2 RNA copies exhaled per minute during natural breathing over the course of COVID-19 infection ➤


❂


📖 (8 Sep 2023 ~ Northwestern University) COVID patients breathe large amounts of virus early on ➤


➲ ‘COVID patients exhale high numbers of virus during the first eight days after symptoms start, as high as 1,000 copies per minute, reports a new Northwestern Medicine study.


On day eight, exhaled levels of virus drop steeply, down to near the limit of detection – an average of two copies exhaled per minute.’


❂


📖 (30 Aug 2023 ~ Nature: News) COVID infection risk rises the longer you are exposed – even for vaccinated people ➤


❂


📖 (19 Aug 2023 ~ Nature: Communications) Evidence of leaky protection following COVID-19 vaccination and SARS-CoV-2 infection in an incarcerated population ➤


❂


📖 (9 Aug 2023 ~ Pre-print) Long COVID in a highly vaccinated population infected during a SARS-CoV-2 Omicron wave – Australia, 2022 ➤


❂


📖 (2 Jun 2023 ~ CIDRAP/University of Minnesota) More than 70% of US household COVID spread started with a child, study suggests ➤


❂


📖 (21 Mar 2023 ~ World Health Network) Doctors Should Not Infect Patients ➤


❂


📖 (15 Mar 2023 ~ Journal of Clinical Medicine) Clinical Outcome and Prognosis of a Nosocomial Outbreak of COVID-19 ➤


❂


📖 (24 Feb 2023 ~ Journal of Hospital Infection) Impact of supplementary air filtration on aerosols and particulate matter in a UK hospital ward: a case study ➤


➲ ‘Collectively, this suggests that appropriately-sized air-cleaning units (ACUs) have the potential to reduce nosocomial infections, especially in inadequately ventilated hospital wards.’


❂

✒ 2022

📖 (16 Dec 2022 ~ JAMA Network Open: Infectious Diseases) Outbreak of SARS-CoV-2 Omicron Infection in a Centralized Quarantine Location in Hangzhou, China ➤


❂


📖 (27 Sept 2022 ~ Twitter) Jeff Gilchrist on Transmission ➤


❂


📖 (1 May 2022 ~ Open Forum Infectious Diseases) Initial Severe Acute Respiratory Syndrome Coronavirus 2 Viral Load Is Associated With Disease Severity: A Retrospective Cohort Study ➤


➲ ‘Higher initial SARS-CoV-2 viral load is associated with an increased risk of hospital admission, ICU admission, and in-hospital mortality.’


❂

✒ 2021

📖 (27 Aug 2021 ~ Science) Airborne transmission of respiratory viruses ➤


➲ ‘There is robust evidence supporting the airborne transmission of many respiratory viruses, including measles virus, influenza virus, respiratory syncytial virus (RSV), human rhinovirus (hRV), adenovirus, enterovirus, severe acute respiratory syndrome coronavirus (SARS-CoV), Middle East respiratory syndrome coronavirus (MERS-CoV), and SARS-CoV-2.


A growing body of research on COVID-19 provides abundant evidence for the predominance of airborne transmission of SARS-CoV-2. This route dominates under certain environmental conditions, particularly indoor environments that are poorly ventilated, an observation that implicates solely aerosols because only aerosols – and not large droplets or surfaces – are affected by ventilation.


Additional precautionary measures must be implemented for mitigating aerosol transmission at both short and long ranges, with a major focus on ventilation, airflows, air filtration, UV disinfection, and mask fit.


These interventions are critical strategies for helping end the current pandemic and preventing future outbreaks.’


❂


📖 (27 Aug 2021 ~ Science) Airborne transmission of respiratory viruses ➤


❂


📖 (13 May 2021 ~ Wired) The 60-Year-Old Scientific Screw-up That Helped Covid Kill ➤


‘All pandemic long, scientists brawled over how the virus spreads. Droplets! No, aerosols! At the heart of the fight was a teensy error with huge consequences.’


❂


📖 (4 May 2021 ~ Forbes) WHO Finally Admits Coronavirus Is Airborne. It's Too Late ➤


‘Over a year since declaring Covid-19 a pandemic, the World Health Organization has finally admitted that Coronavirus is airborne.’


❂


📖 (29 Mar 2021 ~ El País) Avoiding coronavirus infection in indoor spaces: don't breathe other people's air ➤


‘Constant ventilation and permanent control of CO₂ levels are two of the keys to avoiding transmission in closed rooms, as fresh air dilutes the infected particles.’


❂


📖 (25 Mar 2021 ~ Nature: Medicine) SARS-CoV-2 infection of the oral cavity and saliva ➤


❂


📖 (11 Mar 2021 ~ El País) Coronavirus: How infected air can flow from one apartment to another ➤


‘In Spain, the bathrooms of older buildings are connected through communal ducts that allow aerosol exchanges. Although not common, it is suspected that transmission may occur in specific circumstances.’


❂

✒ 2020

📖 (30 Oct 2020 ~ Science) The Science of Superspreading ➤


‘Why preventing hotspots of transmission is key to stopping the COVID-19 pandemic.’


❂


📖 (28 Oct 2020 ~ The Guardian) Understanding 'aerosol transmission' could be key to controlling coronavirus ➤


‘We should still wash our hands, but growing evidence suggests one of the main ways Covid-19 spreads is through the air.’


❂


📖 (25 Aug 2020 ~ Time) COVID-19 Is Transmitted Through Aerosols. We Have Enough Evidence, Now It Is Time to Act ➤


❂


📖 (20 Aug 2020 ~ The Conversation) Poor ventilation may be adding to nursing homes' COVID-19 risks ➤


‘Why are so many aged-care residents and staff becoming infected with COVID-19?


New research suggests poor ventilation may be one of the factors. RMIT researchers are finding levels of carbon dioxide in some nursing homes that are more than three times the recommended level, which points to poor ventilation.’


❂


📖 (25 Jun 2020 ~ Journal of Infection) Viral dynamics of SARS-CoV-2 in saliva from infected patients ➤


❂


📖 (17 Jun 2020 ~ The Conversation) I study coronavirus in a highly secured biosafety lab – here's why I feel safer here than in the world outside ➤


❂


📖 (27 May 2020 ~ Science) Reducing transmission of SARS-CoV-2 ➤


➲ ‘A large proportion of the spread of coronavirus disease 2019 (COVID-19) appears to be occurring through airborne transmission of aerosols produced by asymptomatic individuals during breathing and speaking.


Aerosols can accumulate, remain infectious in indoor air for hours, and be easily inhaled deep into the lungs.’


❂


📖 (14 Mar 2020 ~ Wired) They Say Coronavirus Isn't Airborne – But It's Definitely Borne By Air ➤


‘The word ‘airborne’ means different things to different scientists, and that confusion needs to be addressed.’


❂